Charcot-Marie-Tooth Disease
Definition And Epidemiology
- Charcot-Marie-Tooth disease is the most common hereditary neuropathy.
- It is the most common peripheral neuropathy overall in children.
- It is classified as a primary hereditary neuropathy affecting the peripheral nerves.
- The disease primarily affects the lower motor neuron unit.
- It is also referred to as hereditary motor sensory neuropathy.
- The overall prevalence of the most common demyelinating variant is approximately 3.8 cases per 100,000 population.
- It accounts for more than 50 percent of all hereditary motor sensory neuropathy cases.
Clinical Manifestations
Onset And Progression
- The disease has an insidious onset.
- It follows a slowly progressive course over many years.
- Most patients remain asymptomatic until late childhood or early adolescence.
- Young children sometimes manifest gait disturbances as early as the second year of life.
Motor Symptoms
- Weakness predominantly affects the distal muscles.
- The peroneal and tibial nerves are the earliest and most severely affected.
- Affected children are often described as being clumsy.
- They experience progressive gait difficulties, frequent falls, and tripping over their own feet.
- Progressive weakness of ankle dorsiflexion leads to eventual foot drop.
- The lower legs develop marked thinning, leading to a classic 'stork leg' appearance.
- This unique atrophy is also described as an 'inverted champagne bottle' appearance.
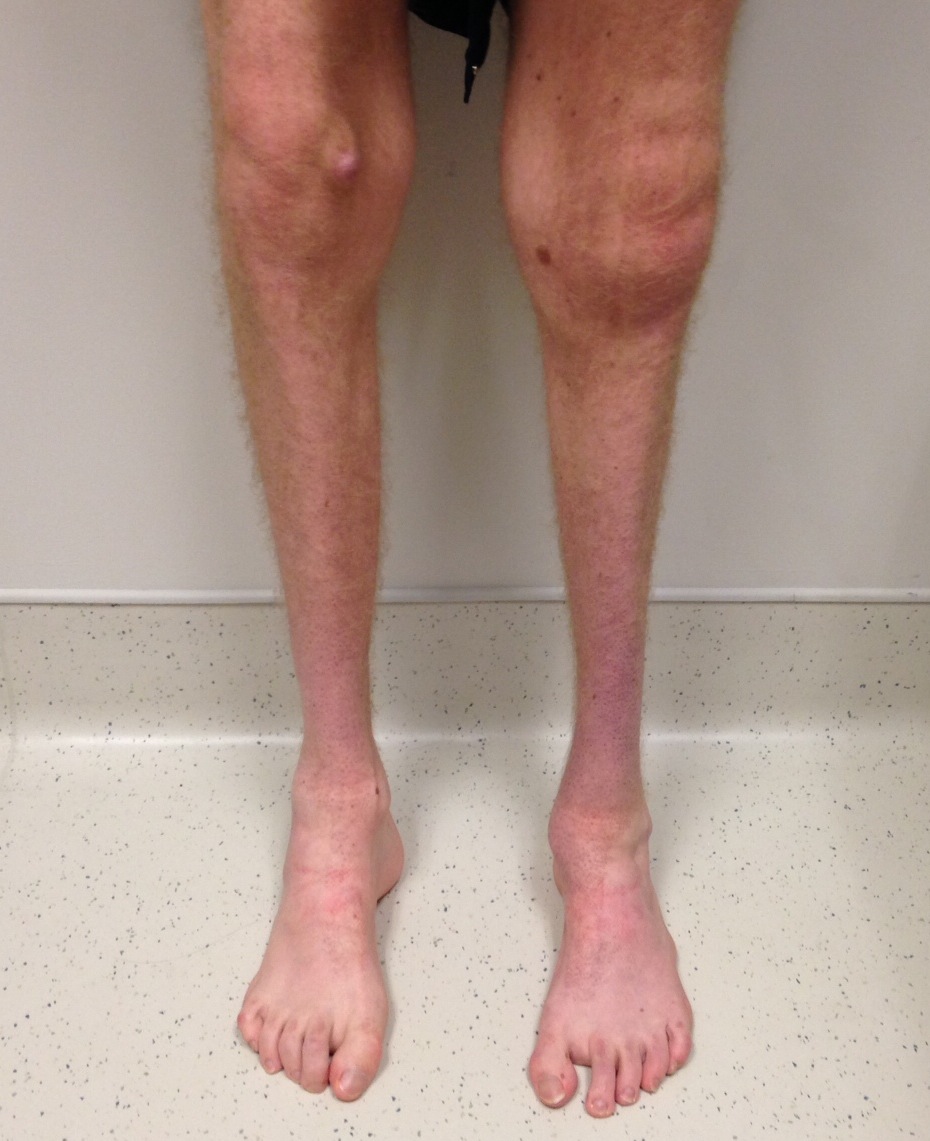
- Upper limb involvement occurs later in the disease course.
- This includes atrophy of the thenar and hypothenar muscles.
- Advanced cases demonstrate clawing of the fingers and contractures of the wrists.
- Proximal muscle weakness is a late manifestation and is usually mild.
Sensory And Autonomic Symptoms
- Prominent sensory signs are present even in the absence of prominent sensory symptoms.
- Sensory involvement mainly affects large, myelinated nerve fibers.
- This leads to a loss of proprioceptive information and vibratory sense.
- The threshold for pain and temperature can also increase.
- Children may complain of tingling or burning sensations in the feet, but pain is rare.
- Autonomic manifestations may be expressed as poor vasomotor control.
- This can lead to blotching or pallor of the skin of the feet and inappropriately cold feet.
Associated Features
- Pes cavus foot deformities are a hallmark and prominent clinical feature.
- Hammer toe deformities are also commonly observed.
- Deep tendon reflexes are hyporeflexic or completely depressed due to lower motor neuron involvement.
- Reflexes are typically lost distally.
- Peripheral nerves often become palpably enlarged at an early age.
- A positive family history is a critical clue pointing towards an inherited neuropathy.
Classification And Genetics
- The disease exhibits vast genetic heterogeneity with more than 140 genes implicated.
- The classification is broadly divided into demyelinating, axonal, and severe infantile forms.
| Disease Subtype | Inheritance Pattern | Gene Or Locus | Pathophysiology And Clinical Features |
|---|---|---|---|
| Charcot-Marie-Tooth 1A | Autosomal dominant | Duplication at 17p11.2 (PMP22) | Most common subtype (70% of CMT1). Uniform conduction velocity slowing below 38 m/s. Demyelinating pattern. |
| Charcot-Marie-Tooth 1B | Autosomal dominant | Mutation at 1q21-q23 (MPZ) | Demyelinating pattern. Gene product is myelin protein zero. |
| Charcot-Marie-Tooth 2A | Autosomal dominant | Mutation at 1p36 (MFN2) | Most common axonal form. Relatively normal nerve conduction velocities. Predominantly reduced action potential amplitudes. |
| Charcot-Marie-Tooth 3 (Dejerine-Sottas) | Autosomal dominant or recessive | 17p11.2 (PMP22) or 1q21-q23 (MPZ) | Severe demyelinating form. Onset in infancy or the first year of life. Very low motor conduction velocity. |
| Charcot-Marie-Tooth 4 | Autosomal recessive | Multiple genes (e.g. GDAP1) | Childhood onset. Usually severe presentation. Contains both demyelinating and axonal types. |
| Charcot-Marie-Tooth X | X-linked dominant or recessive | Mutation at Xq13 (Connexin 32) | Axonal and demyelinating features. Males are more severely affected. Central nervous system involvement is common. |
Diagnostic Evaluation
Clinical And Electrophysiological Studies
- A detailed clinical history is required to identify insidious distal weakness, foot deformities, and familial patterns.
- Electrophysiological studies, including nerve conduction velocity and electromyography, are the primary modalities to classify the disease.
- These studies provide objective data to distinguish demyelinating forms from axonal forms.
| Electrophysiological Property | Demyelinating Pattern (e.g. CMT 1 and 3) | Axonal Pattern (e.g. CMT 2) |
|---|---|---|
| Distal Latency | Increased (prolonged). | Normal. |
| Conduction Velocity | Decreased (reduced). | Normal. |
| Action Potential Amplitude | Normal. | Decreased (reduced). |
| Conduction Block | Absent in hereditary forms. | Absent. |
| Temporal Dispersion | Absent in hereditary forms. | Absent. |
Genetic And Histological Testing
- Genetic testing is useful and necessary for confirming the exact genetic diagnosis and subtype.
- The definitive molecular genetic diagnosis may easily be made using a blood sample.
- A sural nerve biopsy is diagnostic and reserved for cases where genetic testing is inconclusive.
- Biopsies of demyelinating forms reveal characteristic onion bulb formations.
- These formations represent cycles of demyelination and remyelination using Toluidine blue staining.
- This pathologic finding is termed interstitial hypertrophic neuropathy.
- Biopsies of axonal forms reveal axonal degeneration rather than primary demyelination.
- The cerebrospinal fluid protein may be elevated, but no cells appear in the fluid.
Differential Diagnosis
- Distinguishing Charcot-Marie-Tooth disease from other acute and chronic neuropathies is essential.
| Condition | Distinguishing Clinical Features |
|---|---|
| Friedreich Ataxia | Shows areflexia and distal weakness similar to Charcot-Marie-Tooth disease. Differentiated by clear ataxia, loss of joint position sense, and a sensory neuropathy pattern on neurophysiology. |
| Guillain-Barré Syndrome | Acute onset over hours to days. Presents with ascending, bilaterally symmetrical flaccid weakness. Frequently has an antecedent infectious trigger. |
| Chronic Inflammatory Demyelinating Polyneuropathy | Subacute to chronic progression. Involves both proximal and distal weakness. Concomitant sensory loss is present. |
| Spinal Muscular Atrophy | Presents with tongue fasciculations and polyminimyoclonus. Face is relatively spared. Sensory pathways are unaffected. |
Management And Genetic Counseling
- Supportive care remains the standard of therapy for this disease.
- There is currently no effective specific pharmacologic or genetic treatment available in clinical practice.
Physical Therapy And Orthotics
- Regular physical therapy is required to maintain mobility.
- It is crucial for preventing contractures and managing progressive distal weakness.
- Progressive resistance exercise for foot dorsiflexion may attenuate the progression of weakness.
- The lower legs should be protected from traumatic injury.
- Orthotic appliances are frequently required to stabilize the ankles and support ambulation.
- Stiff boots that extend to the midcalf often suffice in the early stages of the disease.
- Lightweight plastic splints, which can be worn inside socks, are custom-made to extend beneath the foot and around the back of the ankle.
- External short-leg braces or ankle-foot orthotics may be required when foot drop becomes complete.
Pharmacological And Surgical Interventions
- Burning paresthesias of the feet are uncommon but can be abolished by administering phenytoin, carbamazepine, or gabapentin.
- Compression neuropathy during sleep may be prevented by placing soft pillows beneath or between the lower legs.
- Severe foot deformities and hand deformities may require surgical management.
- Soft tissue release, bony foot surgery, or surgical fusion of the ankle may be considered in cases of progressive foot deformity.
Counseling
- Genetic counseling must be offered to the patient’s family.
- Discussions should cover inheritance patterns, recurrence risks, and options for prenatal diagnosis.